

Phase 3 Results of Bepirovirsen Treatment for Chronic Hepatitis B Virus Infection Allow Up to 20% of Treated Individuals to Discontinue All Hepatitis B Therapies
 Paul Y. Kwo, MD, FACG1

1Professor of Medicine and Director of Hepatology, Stanford University, Stanford, CA
This summary reviews Hou J, Lim SG, Buti M, et al. Phase 3 Results of Bepirovirsen Treatment for Chronic Hepatitis B Virus Infection. N Engl J Med. 2026;394(24):2395-2406.
Keywords: Chronic hepatitis B virus infection, beporovirsen, hepatitis B virus therapies.
STRUCTURED ABSTRACT
Question: Can a 24-week finite course of subcutaneous bepirovirsen, an anti-sense oligonucleotide that targets all hepatitis B virus (HBV) transcripts, safely and effectively induce a functional cure in adults with chronic HBV infection who are currently virologically suppressed on stable nucleoside or nucleotide analogue (NA) therapy, allowing up to 20% of individuals to safely discontinue treatment for hepatitis B?
Design: Two identical, duplicate-design, phase 3, multicenter, randomized, double-blind, placebo-controlled trials (B-Well 1 and B-Well 2).
Setting: The trial was conducted internationally across 29 countries spanning Europe, the Asia-Pacific region, and the Americas.
Patients: A total of 1,838 randomized adults (1,834 in the full analysis population) with documented noncirrhotic chronic HBV infection. Eligible patients had been on stable NA therapy for 6 months, with baseline HBV DNA < 90 IU/mL, alanine aminotransferase (ALT) < 2 times upper limit of normal and baseline HBsAg levels > 100 and < 3,000 IU/mL.
Exposure: Patients randomized in a 2:1 ratio to receive either weekly subcutaneous injections of bepirovirsen (300 mg, plus loading doses on days 4 and 11) or a matching placebo for 24 weeks. All patients maintained background NA therapy through week 48. Those who met strict virologic response criteria discontinued NA therapy at week 48.
Outcomes: Primary endpoint: Functional cure at week 72 (24 weeks off all HBV therapies), defined as a sustained HBV DNA level below the lower limit of quantification (LLOQ) < 20 IU/mL or not detected), qualitative HBsAg loss (< 0.05 IU/mL), and no use of rescue medication. Key secondary endpoints: Functional cure rate in the lower baseline HBsAg stratum (< 1,000 IU/mL); proportion of patients maintaining sustained HBV DNA < LLOQ at week 72 after stopping NAs in the overall population and the lower HBsAg stratum.
Data Analysis: Efficacy analyses were performed on the full analysis set. Missing data that prevented efficacy assessment were imputed as non-response.
Funding: The trial was funded by GlaxoSmithKline.
Results: Bepirovirsen achieved a functional cure at week 72 in 20% of patients in B-Well 1 (127/650) and 19% in B-Well 2 (106/570), compared to 0% in both placebo groups (P < 0.001). Functional cure was significantly higher in patients with baseline < HBsAg 1000IU/mL, reaching 25% in B-Well 1 and 28% in B-Well 2 (P < 0.001). In the higher stratum (>1,000 to 3,000 IU/mL), cure rates were 10% and 5%, respectively.
Post-NA discontinuation viral suppression HBV DNA < LLOQ at week 72 was sustained in 23% of bepirovirsen patients across both trials.
In a pooled analysis, active treatment period (weeks 1–24) adverse events occurred in 89% of the bepirovirsen group vs. 65% for placebo. Grade 3 adverse events occurred in 16% of bepirovirsen patients, most commonly presenting as a transient ALT flare (6%). Reversible, treatment-dependent reductions in platelet counts and eGFR were observed, which returned toward baseline off therapy.
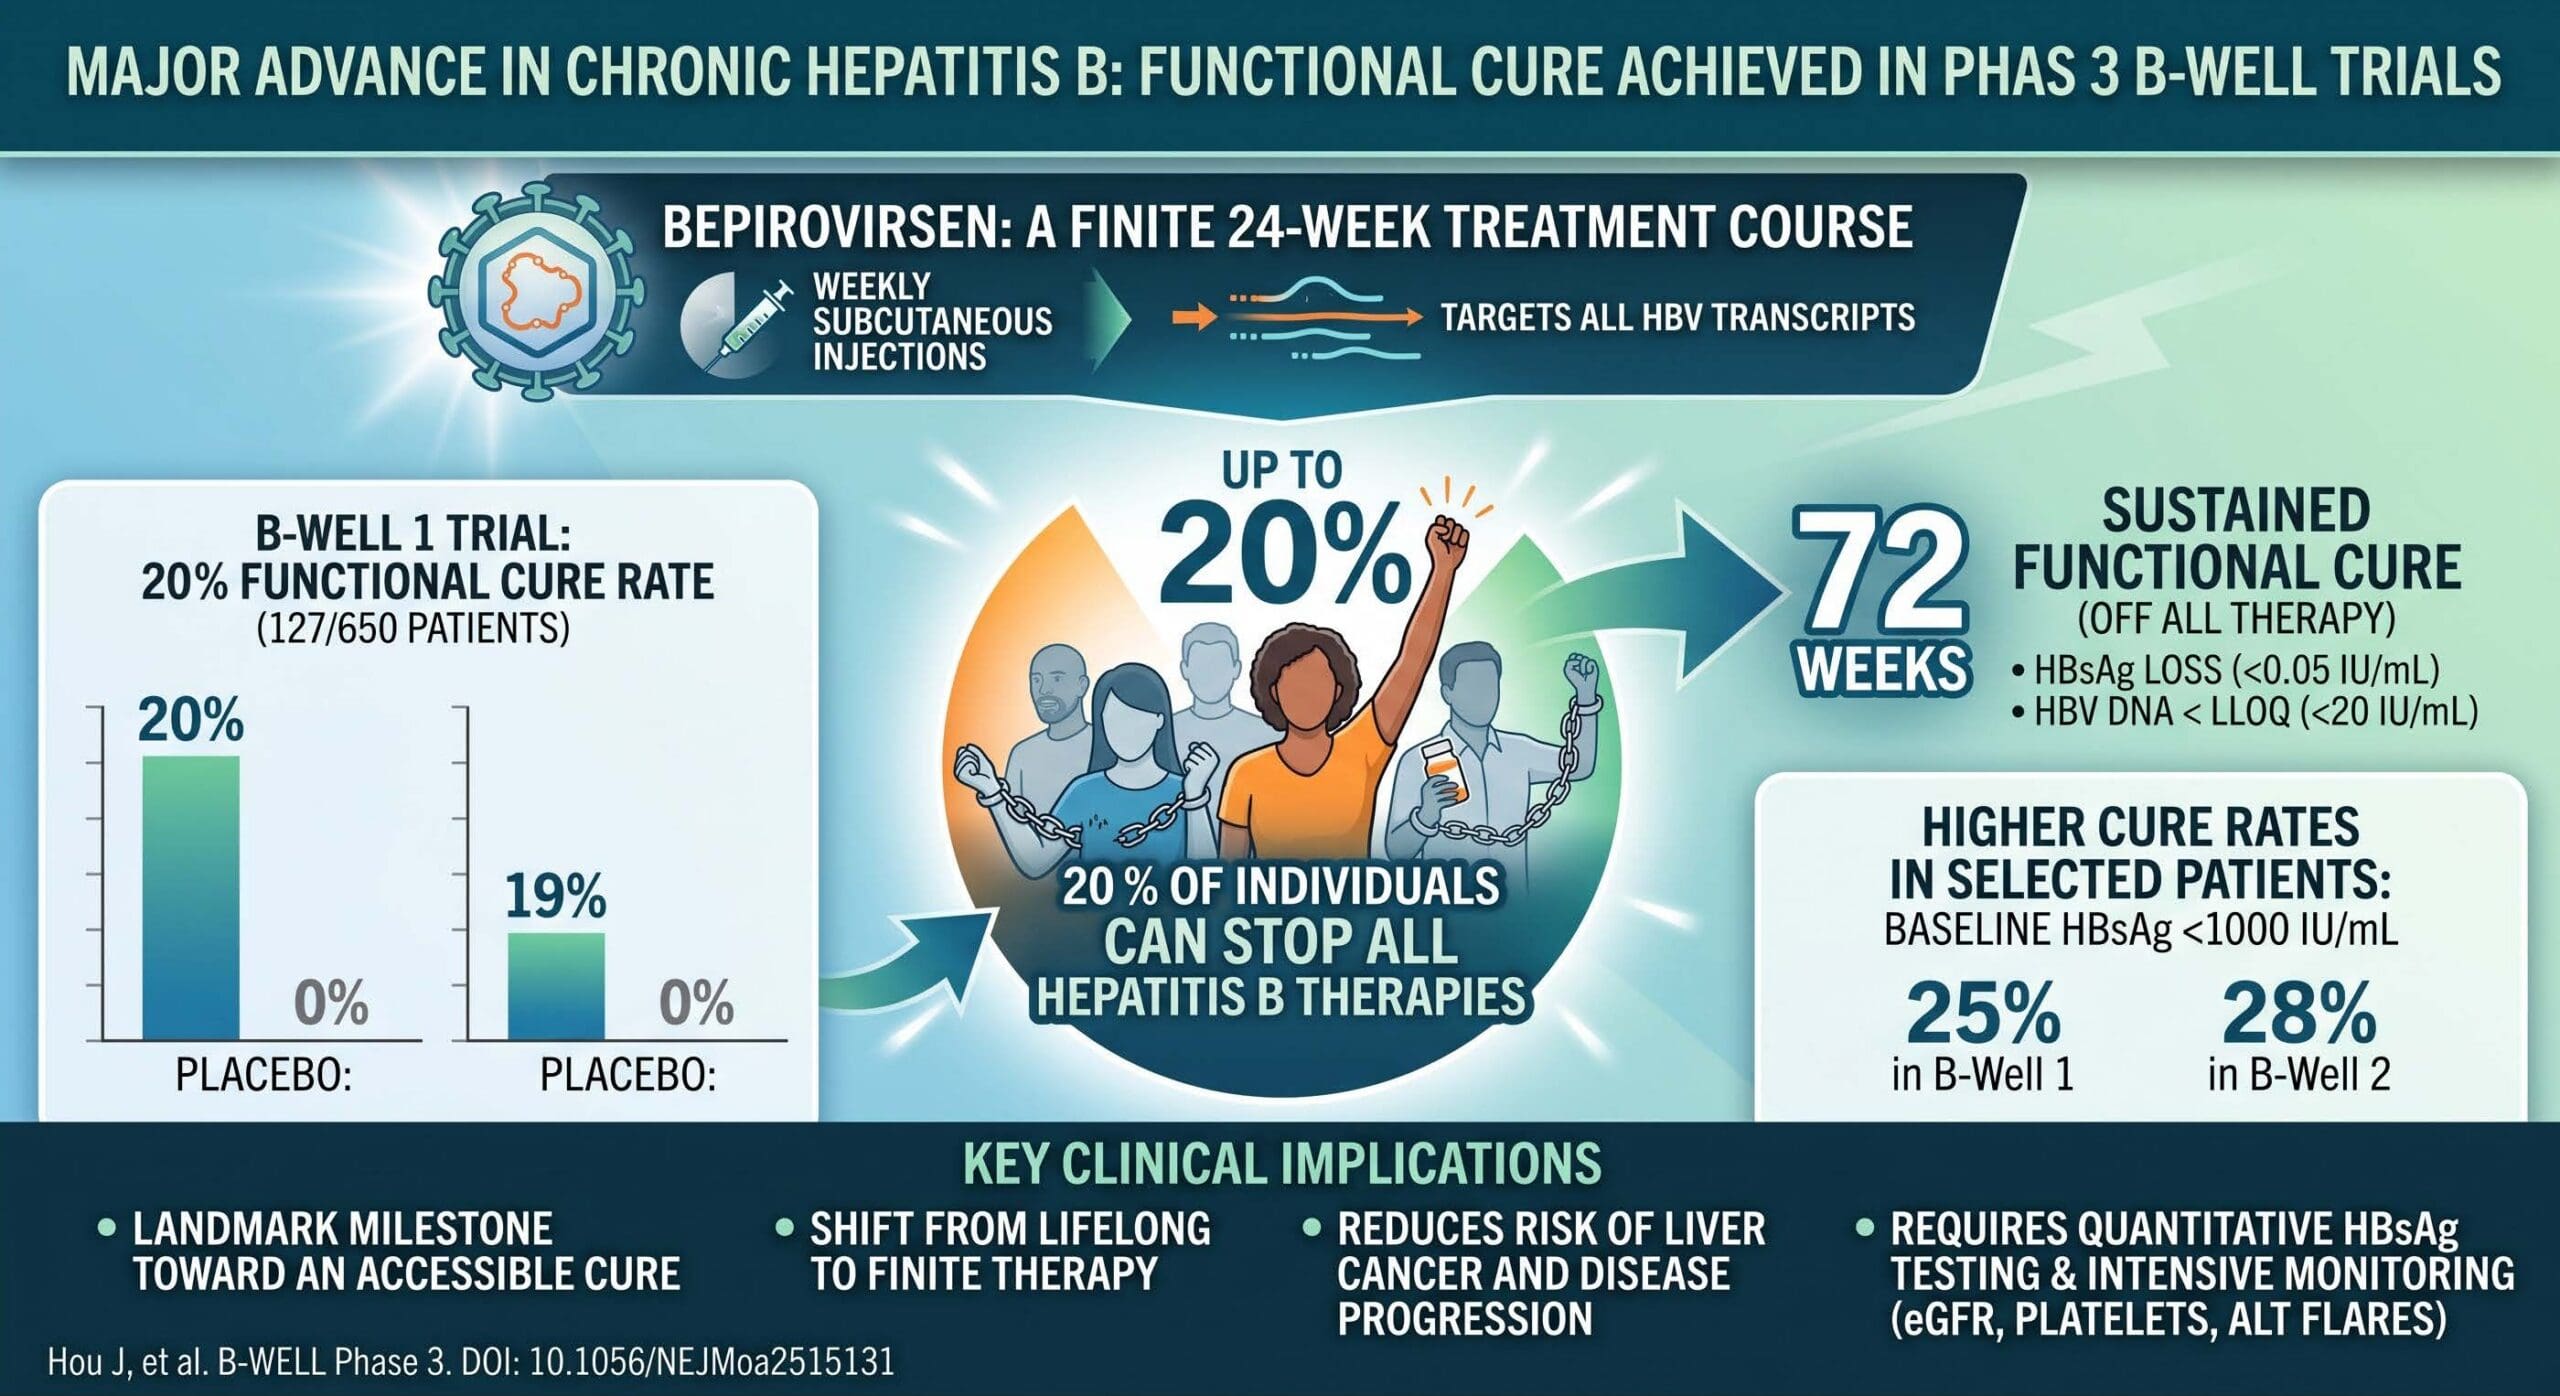
Figure 1. Visual summary of study.
COMMENTARY
Why Is This Important?
Standard oral nucleoside/NA therapies are highly effective at suppressing HBV replication, but they rarely lead to the loss of hepatitis B surface antigen (HBsAg), meaning patients typically face lifelong therapy. A functional cure, characterized by sustained undetectable HBsAg and HBV DNA off treatment, dramatically lowers the risk of developing hepatocellular carcinoma, halts progression of the disease, and removes the continuous burden, financial costs, and adherence risks of lifelong suppressive medication. The B-Well phase 3 trials represent a landmark milestone toward an accessible cure. By adding just 1 investigational agent (bepirovirsen) for a fixed 24-week duration, nearly a fifth of selected patients achieved a functional cure and completely freed themselves from baseline background therapy. The B-Well phase 3 trials represent a significant milestone toward an accessible cure of hepatitis B. By adding a single investigational agent (bepirovirsen) for a fixed 24-week duration, nearly a fifth of selected patients achieved a functional cure and completely freed themselves from baseline background therapy.
Key Study Findings
Caution
While these results are highly encouraging, clinical limitations remain. The current efficacy profiles cannot be generalized to patients outside the trial design criteria, specifically those with advanced cirrhosis, coinfections (HIV, hepatitis C virus, or hepatitis D virus), or high baseline surface antigen levels (>3,000 IU/ml). Furthermore, antisense oligonucleotides carry known class side effects. Active therapy requires rigorous clinical and laboratory surveillance due to a 16% incidence of Grade 3 adverse events (most commonly increased ALT levels) and temporary, drug-induced declines in estimated glomerular filtration rate (eGFR) and platelet counts. There was close monitoring in the trial (every 1-2 weeks), and a similar approach will be required in practice.
My Practice
The potential introduction of bepirovirsen as an option to achieve functional cure will change my practice and the practice of those who care for those with chronic hepatitis B substantially. For selected individuals now, there will be an option to transition individuals who previously committed to lifelong nucleoside/nucleotide analog therapy to the potential for a finite treatment with an approximately 20% chance to safely and permanently discontinue treatment. While at Stanford, our HBsAg automatically reflexes to a quantitative index (signal of the cutoff ratio) to give an approximate quantitative level, we will now need to adopt quantitative surface antigen testing to identify ideal candidates for this treatment (less than or equal to 1,000 international units/mL) as they exhibit the highest clinical response with functional cure rates reaching 25% to 28%. While oral NAs are well tolerated with minimal monitoring, bepirovirsen will require more intensive laboratory monitoring, and our practice will adapt by performing regular blood work every 1 to 2 weeks, depending on the monitoring guidance. We will need to monitor platelet counts and renal function (eGFR), and we will gain further experience managing ALT flares, which signal immune-mediated clearance of infected cells. We will also need to establish strict milestones to determine who can successfully stop their NA therapy, which will mirror the trial where loss of hepatitis B surface antigen from week 24-46 can proceed with discontinuation of NA therapy at week 48 and an evaluation of functional cure at week 72.
For Future Research
To optimize the real-world utility of bepirovirsen, future prospective research must establish the true durability of this functional cure over extended, multi-year timelines. Moreover, bepirovirsen will likely serve as the backbone on which other combination therapy strategies are designed to push functional cure rates beyond the 20% mark and expand functional curative options for a wider hepatitis B population. Investigating sequential or combination therapies will be crucial.
Conflict of Interest
The author of the summary declares no conflicts of interest.