

Family-Based Obesity Treatment in Primary Care: An Upstream Strategy for Metabolic and Liver Health
 Yifei Hu, MD, PhD1 and Sten H. Vermund, MD, PhD2

1Pediatric Epidemiologist, School of Public Health, Capital Medical University, Beijing, China
2University of South Florida College of Public Health, Tampa FL USA
This summary reviews Staiano AE, Cook SR, Stein RI, et al. Family-centered child obesity treatment: the TEAM UP randomized clinical trial. JAMA Pediatr. 2026. doi:10.1001/jamapediatrics.2026.3067.
Keywords: Childhood obesity, family-based behavioral treatment, primary care, pediatric obesity, metabolic health, percent median BMI
STRUCTURED ABSTRACT
Question: Among children and adolescents with obesity receiving care in primary care practices, does adding family-based behavioral treatment (FBT) to enhanced standard of care (ESOC) improve weight outcomes compared with ESOC alone?
Design: The study was a pragmatic, multicenter, comparative-effectiveness randomized clinical trial conducted from 2019 to 2024, with blinded outcome assessment and follow-up through 18 months.
Setting: The trial was conducted in 41 primary care clinical practices in Louisiana, New York, Missouri, and Illinois, reflecting real-world pediatric obesity care.
Patients: A total of 730 parent-child dyads were randomized. Eligible children were aged 6 to 15 years with obesity, defined as body mass index at or above the 95th percentile for age and sex. The cohort was socioeconomically diverse: 46.6% were insured by Medicaid and 22.1% lived in households reporting food insecurity. Children with significant eating disorder symptoms or medical conditions substantially affecting growth, appetite, weight, or physical activity were excluded.
Intervention: All participants received ESOC, a primary care practitioner-led obesity management program based on American Academy of Pediatrics guidance and intensified according to clinical response over 12 months. The intervention group additionally received structured FBT delivered by trained interventionists, emphasizing healthy eating, physical activity, behavioral self-management, positive parenting strategies, and modification of home and social environments.
Outcomes: The primary outcome was changed in percent over median body mass index (BMI), or percent median BMI, from baseline to 12 months. Secondary and exploratory outcomes included additional BMI metrics, the proportion achieving a clinically meaningful BMI z-score reduction of at least 0.25, child and parent-reported quality of life, cardiometabolic measures, parent weight change, and adverse events.
Data Analysis: Analyses were conducted using an intention-to-treat framework. Linear mixed-effects models evaluated treatment effects while adjusting for site, child age, sex, and race. Completer, tipping-point, and preplanned sensitivity analyses were performed to assess robustness.
Funding: The trial was funded primarily by the Patient-Centered Outcomes Research Institute, with additional institutional and National Institutes of Health support. Funders had no role in study design, conduct, or reporting.
Results: Among 723 analyzed participants, mean age was 10.8 years, 53.5% were female, 46.6% were insured by Medicaid, and 22.1% lived in households with food insecurity. At 12 months, children receiving ESOC+FBT achieved a significantly greater reduction in percent median BMI than those receiving ESOC alone, with a between-group difference of -3.8 units (95% CI, -6.20 to -1.34; P = 0.002). Benefits were evident by 6 months and persisted through 18 months, with a between-group difference of -4.3 units at 18 months (95% CI, -7.25 to -1.41). Nearly half of ESOC+FBT children met the clinically meaningful BMI z-score reduction threshold at 18 months, and weight-related quality of life improved more in the ESOC+FBT group at the end of treatment. No adverse events were deemed related to trial participation.
In this pragmatic primary care trial, adding family-based behavioral treatment to enhanced standard obesity care produced greater and more durable reductions in relative weight than enhanced standard care alone. These findings demonstrate that evidence-based, family-centered obesity treatment can be implemented in routine primary care settings serving geographically and socioeconomically diverse populations. For gastroenterology (GI) and hepatology clinicians, the study supports earlier intervention on pediatric obesity before obesity-related metabolic and liver complications become established.
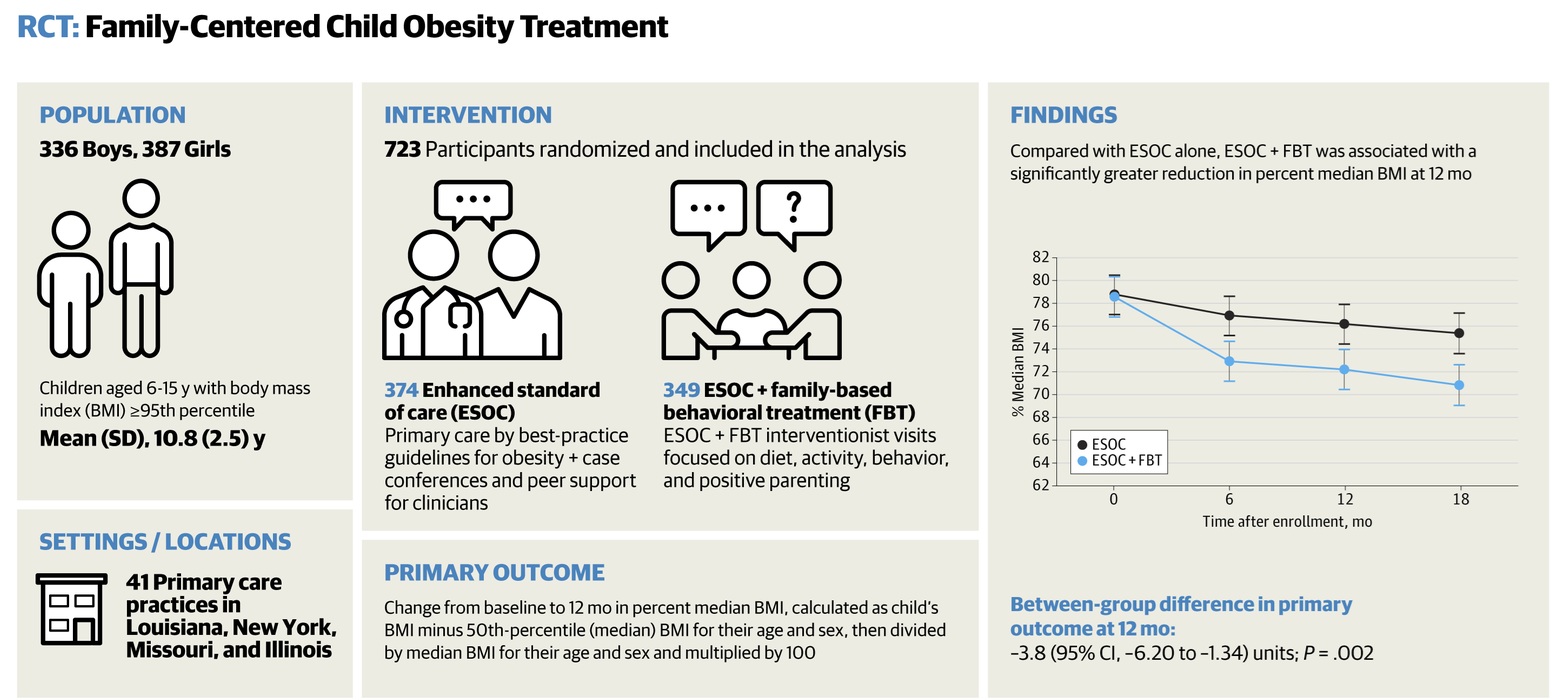
Figure 1. Visual abstract for RCT: Family-centered child obesity treatment.
Reused from Staiano et al under a CC-BY-NC-ND.1
COMMENTARY
Why Is This Important?
Childhood obesity affects approximately 1 in 5 US children and adolescents and is an upstream driver of cardiometabolic disease, impaired quality of life, and future obesity-related liver disease.1 For gastroenterologists and hepatologists, childhood obesity is not only a pediatric primary-care issue; it is an early determinant of metabolic dysfunction-associated steatotic liver disease (MASLD), cardiometabolic risk, and future adult digestive disease burden. TEAM UP is therefore relevant to GI practice because it tests whether an evidence-based obesity intervention can be delivered earlier, closer to where families receive routine care, and before obesity-related liver and metabolic complications become entrenched.
The 2023 AAP clinical practice guideline recommends intensive health behavior and lifestyle treatment, including at least 26 contact hours over 3 to 12 months, for children aged 6 years and older with obesity.2,3 Family-based behavioral treatment is a well-validated example of this approach,4,5 but it has historically been delivered in specialty research clinics and remains unavailable to many families. TEAM UP addresses a pragmatic and policy-relevant question: can structured FBT be embedded within primary care and still produce meaningful benefit in a geographically and socioeconomically diverse population?
The trial is especially important because it included 41 real-world primary care practices and enrolled a broad population, including nearly half of children insured by Medicaid and more than 1 in 5 from households experiencing food insecurity. This makes the findings more relevant to routine pediatric obesity care than many efficacy trials conducted in specialized academic settings.
Key Study Findings
The trial also demonstrates that meaningful pediatric obesity treatment need not be confined to specialty centers. ESOC+FBT was delivered in primary care settings, with trained interventionists focusing on healthy eating, physical activity, positive parenting, behavioral skills, and management of social and environmental cues. For GI clinicians, the message is upstream prevention: earlier, family-centered obesity treatment may help reduce later metabolic and liver disease burden.
Caution
Several features temper interpretation. Enrollment and treatment delivery were disrupted by the COVID-19 pandemic, prompting a mid-trial reduction in target sample size from 1,296 to 728 dyads. The study retained power for the primary endpoint but not for prespecified race-by-sex interaction analyses.
Treatment dose is also central to interpretation. Although 26 to 33 FBT sessions were planned,3,6 mean attendance was 16.7 sessions, and attendance was lower among African American children, Medicaid-insured children, and families with food insecurity. This cuts both ways: the observed effect is impressive despite incomplete treatment exposure, but real-world uptake barriers may limit population-level impact if flexible delivery models are not built into implementation. The attendance pattern should be interpreted as evidence of structural barriers, not as lack of family motivation.
ESOC was also an enhanced, trained, guideline-based comparison condition rather than ordinary unstructured primary care, so the incremental benefit of FBT should not be interpreted as a comparison against minimal care. The primary outcome was a relative-weight measure over 12 months rather than a hard cardiometabolic or long-term liver endpoint, and most secondary outcomes were exploratory and not adjusted for multiplicity. Height and weight were sometimes collected remotely or extracted from the medical record, representing about 21% of follow-up data, although a within-trial validation study supported concordance. Finally, families were referred by their primary care practitioner or self-selected into the trial, which may limit generalizability to less motivated or less connected populations.
Our Practice
In GI and hepatology practice, TEAM UP reinforces the importance of treating pediatric obesity as an early, modifiable risk factor for future metabolic and liver disease rather than waiting until adolescents present with established MASLD or cardiometabolic complications.7,8 When counseling families, we emphasize that intensive behavioral treatment is not simply “diet advice.” In TEAM UP, FBT included structured nutrition and physical activity plans, positive parenting, self-monitoring, goal setting, problem-solving, and attention to the home and social environment.
Engagement is a clinical problem to solve rather than a patient or family failing. The lower attendance observed among African American children, Medicaid-insured children, and families with food insecurity suggests that clinicians should treat missed visits as a signal of structural barriers. In practice, that means screening for social needs, offering telehealth and flexible scheduling when feasible, coordinating with primary care and behavioral health teams, and advocating for reimbursement models that make intensive behavioral treatment accessible. Telehealth and flexible delivery deserve particular attention because the draft notes that better attendance and outcomes were associated with flexible approaches.
For adolescents with more severe obesity or comorbidities, pharmacologic adjuncts, including glucagon-like peptide-1 receptor agonists, may be relevant complements to intensive behavioral treatment. However, TEAM UP reinforces that behavioral treatment remains foundational and should not be displaced by medication alone.9 I would frame the clinical goal as improving health trajectories, quality of life, and future metabolic and liver risk, while remaining attentive to weight stigma and emerging disordered eating concerns.
For Future Research
Future research should test scalable implementation models that embed FBT into routine primary care while reducing attendance gaps for families facing structural barriers. Head-to-head comparisons of telehealth, hybrid, and in-person delivery models are needed to determine how to optimize engagement without diluting treatment effects.
GI-relevant future studies should assess whether early family-based obesity treatment reduces incident MASLD, improves liver enzymes or imaging-based steatosis and fibrosis measures, and delays or prevents adolescent referral for obesity-related liver disease. Longer-term follow-up is also needed to assess durability of weight change, cardiometabolic outcomes, quality of life, and the best sequencing or combination of intensive behavioral treatment with pharmacotherapy. Multidisciplinary care models linking primary care, gastroenterology/hepatology, nutrition, behavioral health, and community support may be especially important for translating TEAM UP from trial evidence into population health benefit.
Conflict of Interest
The authors of the summary declare no conflicts of interest.
REFERENCES
- Staiano AE, Cook SR, Stein RI, et al. Family-Centered Child Obesity Treatment: The TEAM UP Randomized Clinical Trial. JAMA Pediatr. 2026.
- Hampl SE, Hassink SG, Skinner AC, et al. Clinical practice guideline for the evaluation and treatment of children and adolescents with obesity. Pediatr. 2023;151(2):e2022060640.
- Force UPST, Nicholson WK, Silverstein M, et al. Interventions for high body mass index in children and adolescents: US Preventive Services Task Force recommendation statement. JAMA. 2024;332(3):226-232.
- Wilfley DE, Stein RI, Saelens BE, et al. Efficacy of maintenance treatment approaches for childhood overweight: A randomized controlled trial. JAMA. 2007;298(14):1661-1673.
- Epstein LH, Wilfley DE, Kilanowski C, et al. Family-based behavioral treatment for childhood obesity implemented in pediatric primary care: A randomized clinical trial. JAMA. 2023;329(22):1947-1956.
- O’Connor EA, Evans CV, Henninger M, Redmond N, Senger CAJJ. Interventions for weight management in children and adolescents: Updated evidence report and systematic review for the US Preventive Services Task Force. JAMA. 2024;332(3):233-248.
- Shu W, Li M, Xiao H, et al. Validation of “Life’s essential 8” metrics with cardiovascular structural status in children: the PROC study in China. J Am Heart Assoc. 2023;12(12):e029077.
- Yang L, Li M, Zhao M, et al. Resolution of metabolic dysfunction improves liver health among Chinese children: Evidence from two prospective cohorts. Clin Gastroenterol Hepatol 2026;24(6):1635-1643.
- Wan KW, Lei EFC, Liu Y, et al. Obesity Management Pharmacotherapies and Lifestyle Treatment for Pediatric Obesity Management: A Systematic Review and Network Meta-Analysis. JAMA Pediatr. 2026. doi:10.1001/jamapediatrics.2026.2248